
Child Meltdown Co-Regulation: 3 Powerful Steps to Calm the Storm
Applying child meltdown co-regulation requires shifting our focus from enforcing verbal compliance to restoring autonomic physical safety when a young child’s emotional and sensory capacity collapses.
Child meltdown co-regulation is an adult-led physiological de-escalation practice. Rather than demanding reasoning from a brain in survival distress, the adult uses calm vocal prosody, grounded physical proximity, and reduced environmental demands to help the child’s nervous system return to baseline.
- Tantrum vs. Meltdown: Why the Difference Dictates the Action
- The Biology of the Freeze-Flight Surge
- The 3-Step Child Meltdown Co-Regulation Protocol
- What NOT to Do: 4 Critical De-escalation Traps
- The Post-Storm Window: Rebuilding Without Interrogation
- Connected Guides in the Regulation Cluster
- Academic References & Scientific Sources
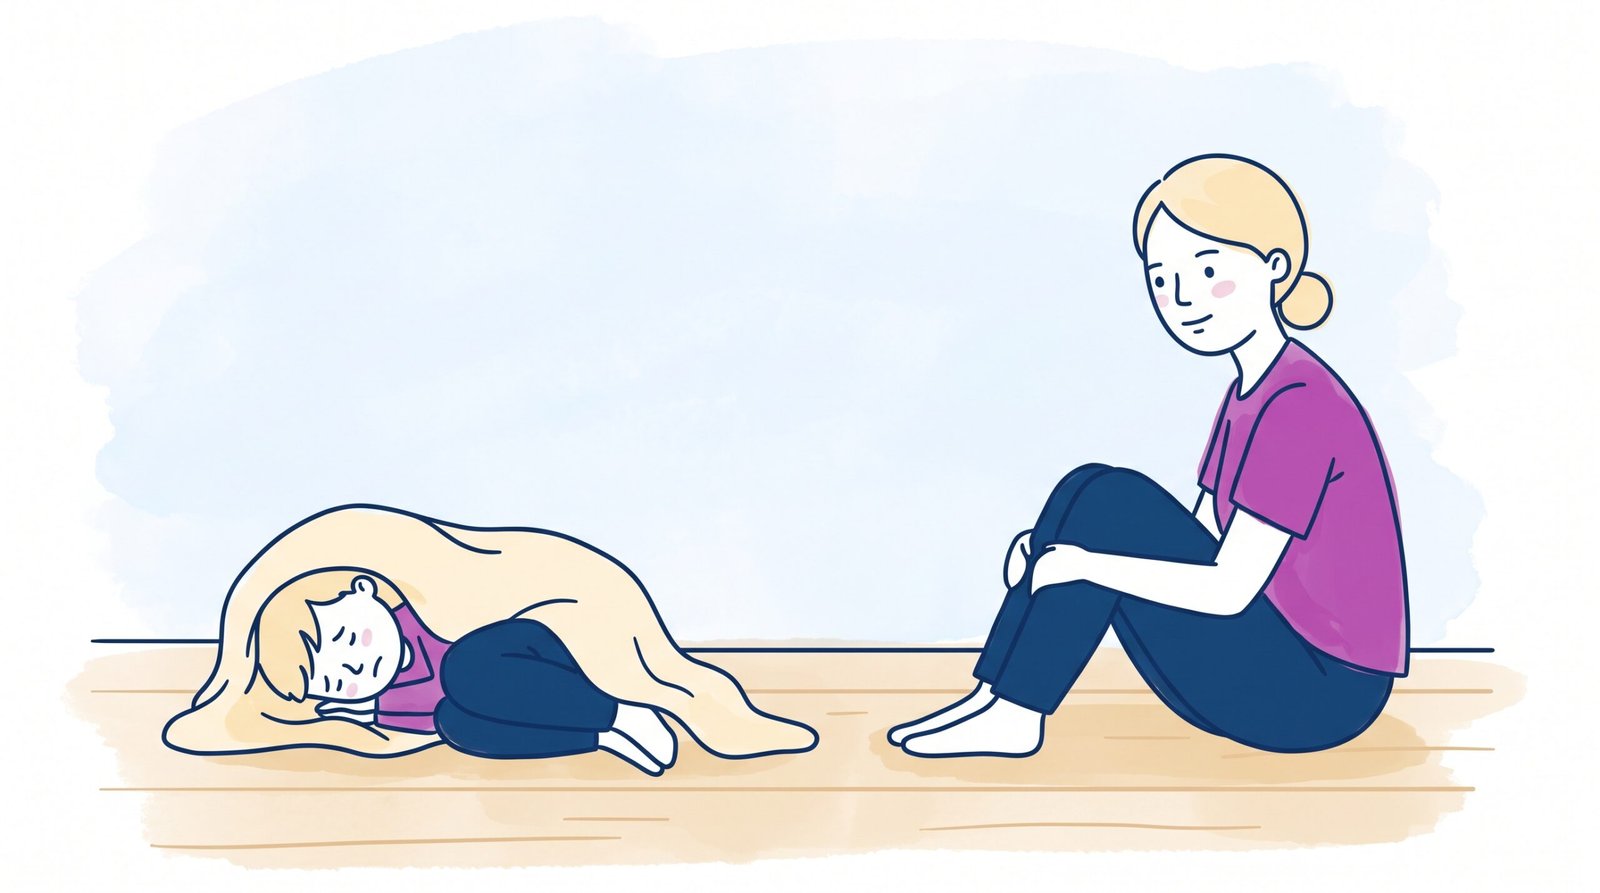
Tantrum vs. Meltdown: Why the Difference Dictates the Action
The single biggest barrier to effective child meltdown co-regulation is mistaking an involuntary neurological meltdown for an operant behavioural tantrum.
A tantrum is goal-oriented. A child wants a specific biscuit at the supermarket, an extra turn on the tablet, or to avoid packing away a puzzle. In a tantrum, the prefrontal cortex remains largely operational: the child checks to see if an adult is looking, adjusts their volume based on audience reaction, and can cease the behaviour immediately if the desired object is provided.
A neurological meltdown is entirely different. It represents an involuntary collapse of autonomic regulation. The sensory, emotional, or cognitive demands placed on the child have exceeded their neurological capacity. In this state, the child is not trying to get something; they have lost control of their own body. Giving them the toy or biscuit will not stop the storm because the surge has already taken hold.
| Observable Marker | Behavioural Tantrum | Neurological Meltdown |
|---|---|---|
| Primary Origin | Frustration over an unmet conscious desire. | Sensory overload, executive fatigue, or intense autonomic threat. |
| Prefrontal Gating | Intact; the child monitors social cues and adult responses. | Offline; survival circuitry has overridden conscious cortical thinking. |
| Safety Awareness | Present; the child rarely harms themselves or damages treasured items. | Impaired; the child may run into traffic, thrash blindly, or drop to the ground. |
| Resolution Trigger | Resolves quickly when a boundary holds or a compromise is struck. | Only resolves when the autonomic nervous system physically recovers. |
Treating a neurological meltdown like a tantrum—by using time-outs, issuing warnings, or offering sticker bribes—only adds more cognitive pressure to an already overloaded brain. To support the child, our approach must centre on somatic child meltdown co-regulation.
The Biology of the Freeze-Flight Surge
To implement child meltdown co-regulation smoothly, adults need to understand the internal biological timeline of nervous system arousal.
As demonstrated by developmental research from Harvard’s Center on the Developing Child, acute stress activates the sympathetic branch of the autonomic nervous system. The amygdala sounds a biological alarm, releasing cortisol and adrenaline into the child’s bloodstream.
During this physiological cascade:
- Heart rate and respiration spike to prepare for defensive action.
- Peripheral vision narrows into tunnel focus to isolate perceived threats.
- Auditory processing filters shift away from human vocal ranges and toward high-frequency alarm tones.
- Expressive and receptive language centres (such as Broca’s area) experience functional suppression.[1]
Under Australia’s national early education framework administered by ACECQA, building secure, emotionally responsive environments is foundational. We cannot teach emotional literacy in the middle of a storm; we can only co-regulate the physical body until safety returns.
The 3-Step Child Meltdown Co-Regulation Protocol
When a child tips past their regulatory tipping point, use this 3-step child meltdown co-regulation procedure. It is designed to work in noisy classrooms, busy living rooms, or during high-friction public transitions.
Clear the Field & Lower the Room Load
Your first move has nothing to do with talking to the child; it is about adjusting the room itself. A brain in sympathetic fight-or-flight is hyper-reactive to sound, light, and movement.
- Acoustic Buffer: Immediately turn off background television, amplified music, or humming appliances. Speak in a low, monotone voice only when necessary.
- Visual Calming: Dim overhead fluorescent tubes. Draw blinds or redirect group activities away from the immediate area.
- Physical Safety Perimeter: Quietly guide other children to another space without making an announcement. Move heavy, sharp, or breakable items out of kicking and flailing range.
Sit Down, Drop Demands, and Steady Your Own Body
Children borrow their nervous system state from the adults around them. If an educator stands over a child with hands on hips, breathing rapidly and issuing commands, the child’s neuroception reads “predator” rather than “safety.”
- Drop Your Vertical Stature: Sit directly on the floor. Position yourself at a 45-degree angle rather than squaring off face-to-face, which can feel confrontational.
- Respect Spatial Distance: Maintain roughly 1.5 to 2 metres of space. Do not force physical touch. If the child seeks contact, offer a firm, grounded lap or hand. If touch causes them to flinch or strike out, back off smoothly.
- The Silent Exhale: Take slow, audible, grounding breaths through your nose, exhaling steadily through your mouth. Your calm physiological presence does the heavy lifting of co-regulation before you say a single word.
Use Short, Steady Anchor Words
Because receptive language is heavily impaired during an acute surge, speak only in brief, rhythmic anchor phrases. Keep sentences under five words:
- “You are safe here.”
- “I am right here with you.”
- “No big jobs right now.”
- “Take your time.”
Deliver these phrases every 60 to 90 seconds, followed by periods of calm, patient silence. This provides predictable auditory checkpoints without demanding a reply.
What NOT to Do: 4 Critical De-escalation Traps
In the tension of an unexpected classroom or home crisis, well-intentioned adults often default to habits that accelerate dysregulation. Effective child meltdown co-regulation requires avoiding these four common traps:
- The Interrogation Trap: Asking “Why did you do that?” or “Can you tell me what is wrong?” Demanding verbal explanations from a brain in survival defence only intensifies panic.
- The Consequence Threat: Warning “If you do not sit down right now, you won’t get iPad time tonight.” Future consequences mean nothing to an adrenaline-flooded brain. It simply signals that the adult is another source of danger.
- The Public Shaming Trap: Moving markers to “red” on a behaviour ladder or discussing the meltdown within earshot of siblings or peers. This triggers dorsal vagal shame and prolongs recovery.
- The Premature Comfort Trap: Forcing tight hugs or grabbing the child’s hands when their sensory system is in defensive fight-or-flight. Unless a child explicitly seeks deep pressure, forced touch feels like physical restraint.
The Post-Storm Window: Rebuilding Without Interrogation
Once the peak of the storm passes, a child does not snap straight back to their regular cognitive baseline. They enter a vulnerable “hangover” phase marked by neurochemical exhaustion, physical trembling, and dorsal shame.
Successful child meltdown co-regulation extends into this recovery period:
1. Somatic Replenishment: Offer a cold cup of water with a straw (sucking provides calming oral-motor sensory feedback) or a small snack with protein. Wash their face or hands with a cool cloth if they welcome it.
2. Low-Demand Re-entry: Do not immediately send the child back into high-demand group tasks or make them clean up the scattered blocks right away. Allow ten to fifteen minutes of quiet, parallel activity—such as looking at an illustrated book, manipulating play dough, or resting under a weighted blanket.
3. Narrative Sequencing (Hours Later): Revisit what happened only after their nervous system has fully reset—often hours later or the following morning. Keep it neutral and factual: “Yesterday the room got really noisy, your body felt like a volcano, and everything tumbled over. We kept you safe. Next time it gets that loud, you and I can step over to the quiet corner together.”
• Discover why reward ladders and sticker systems backfire during sensory overload in Why Behaviour Charts Don’t Work for ADHD →
• Learn to identify early somatic warning signs before meltdowns peak in Fight, Flight, and Freeze in Children Decoded →
• Return to our cluster hub for broader strategies on Regulation and Behaviour in Early Childhood →
Academic References & Empirical Frameworks
- van der Kolk, B. A. (2014). The Body Keeps the Score: Brain, Mind, and Body in the Healing of Trauma. Penguin Books. [Neuroimaging data confirming Broca’s area language deactivation during acute sympathetic survival states].
- Porges, S. W. (2011). The Polyvagal Theory: Neurophysiological Foundations of Emotions, Attachment, Communication, and Self-Regulation. W. W. Norton & Company.
- Shanker, S. (2016). Self-Reg: How to Help Your Child (and You) Break the Stress Cycle and Successfully Engage with Life. Penguin Random House.
- Greene, R. W. (2014). Lost at School: Why Our Kids with Behavioral Challenges Are Falling Through the Cracks and How We Can Help Them. Scribner.
- Siegel, D. J., & Bryson, T. P. (2011). The Whole-Brain Child: 12 Revolutionary Strategies to Nurture Your Child’s Developing Mind. Delacorte Press.